
Updated · GetClinicTurkey Editorial · General planning information, not personal medical advice.
Not always. You need a bone graft only if a scan shows there is not enough healthy jawbone, in height or width, to hold an implant in the right position. That is more likely if the tooth was lost long ago, after gum disease, or below the sinus. Grafting is usually a separate cost, so find out before you accept a quote, not in the dental chair.
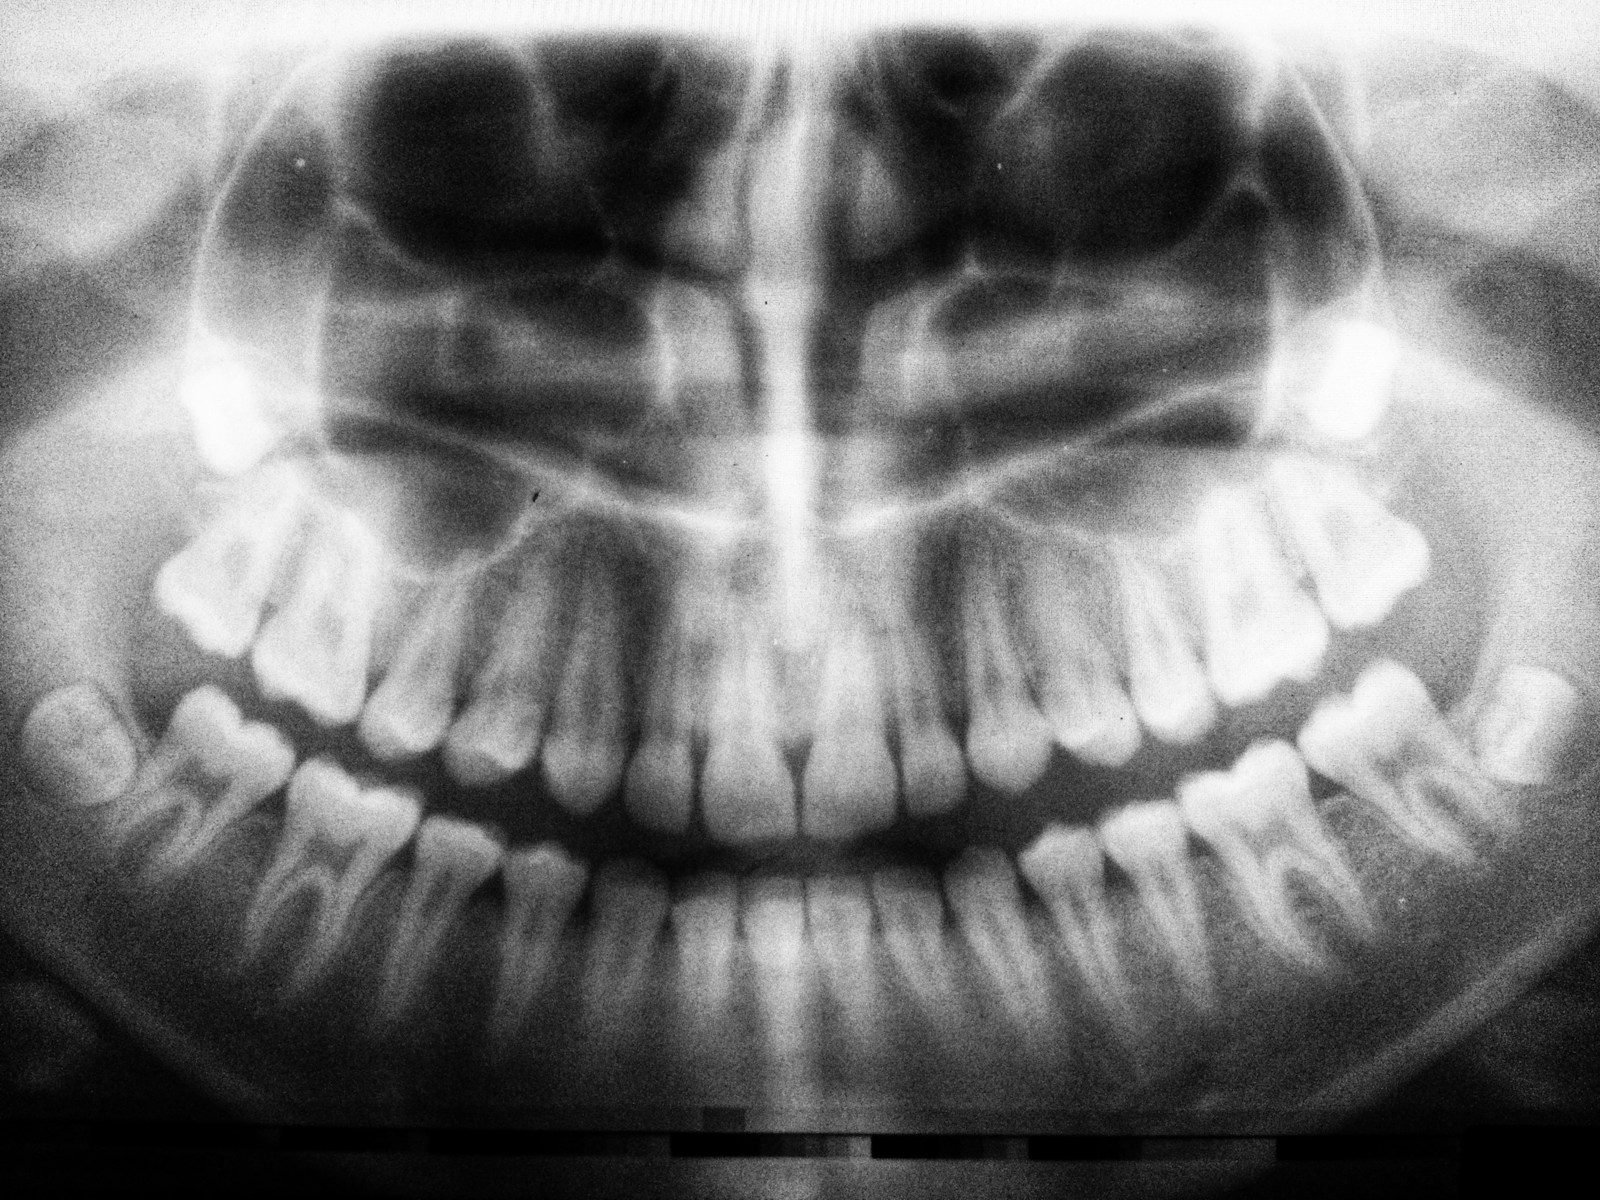
Why the jawbone shrinks after a tooth is lost
Once a tooth has gone, the bone that held it remodels. A systematic review of studies that re-measured extraction sites found horizontal bone loss of 29–63% and vertical loss of 11–22% about six months after extraction, with the fastest change in the first three to six months (Tan et al., 2012). More width is lost than height, and an implant needs bone on all sides.
Gum disease and infection also destroy bone. In the upper back jaw the maxillary sinus sits just above the roots of the back teeth, so the bone under it can be shallow (Lyu et al., 2023). Your general health and smoking also affect whether implants are suitable (Leeds Teaching Hospitals).
How a clinic decides: OPG versus CBCT
Leeds Teaching Hospitals, an NHS implant service, says assessment starts with an examination and X-rays, and that a 3D X-ray, a cone beam CT (CBCT) scan, “is usually requested”. The scan shows the amount of bone and where structures such as neighbouring roots, nerves, the nasal cavity and the sinuses sit (Leeds).
A panoramic X-ray (OPG) is two-dimensional, so it cannot show how wide the ridge is. Treat any quote based only on an OPG or photographs as provisional for anything involving bone.
Before you ask for a quote, send:
- a recent CBCT (full DICOM files, not screenshots) or, failing that, an OPG;
- when each tooth was lost, and any gum disease or infection there;
- smoking, medical conditions and medicines.
If you have no scan, ask whether the clinic will take one before any irreversible work, and what happens to your deposit if the result changes the plan. See what to check before paying a deposit.
Types of bone graft material
Graft material can come from you, from a human donor, from an animal or from a laboratory (CUH). It acts as a scaffold that your body gradually replaces with bone.
| Type | Where it comes from | What to know |
|---|---|---|
| Autograft (your own bone) | Usually the jaw or chin for smaller grafts; for larger reconstructions, the hip or the skull | Described as the reference standard, but it needs a second surgical site, with the pain and risks that brings |
| Allograft (human donor) | Donor bone processed by a tissue bank | No second surgical site |
| Xenograft (animal) | Usually bovine (cattle) or porcine (pig) bone | Widely used in dentistry; no second surgical site |
| Synthetic (alloplast) | Laboratory-made materials such as calcium phosphates and bioactive glasses | No donor tissue involved |
Sources: Cambridge University Hospitals; Ferraz, 2023.
Is one material clearly better? The evidence does not say so. A 2009 Cochrane review of bone augmentation techniques concluded that various techniques can rebuild bone horizontally and vertically, “but it is unclear which are the most efficient”, that complications are common, especially when building bone upwards, and that some bone substitutes could be a preferable alternative to your own bone (Cochrane, 2009); it rested on few, small trials. Ask which material and membrane the clinic will use, and why, and have the product names written in your notes. If you object to animal or donor material, say so before the plan is finalised.
Sinus lift: when the upper back jaw is too shallow
A sinus lift (sinus floor elevation) is a graft for the upper back teeth. The surgeon raises the membrane lining the sinus floor and places graft material beneath it to add height (Lyu et al., 2023; Leeds). There are two main approaches:
- Open, or lateral window: a window is made in the side wall of the sinus to lift the membrane under direct vision. It is the more invasive option, associated with post-operative complications, higher cost and a more complex procedure.
- Closed, or crestal (transcrestal): the membrane is pushed up through the hole prepared for the implant. It is less invasive and quicker, but the surgeon cannot see the membrane.
The choice depends mainly on how much bone is left under the sinus, plus sinus shape and membrane health. One 2023 review (Lyu et al.) favours the crestal approach above 6 mm of remaining bone, and at 4–6 mm if the sinus is healthy, with the lateral approach more often at 2–4 mm. Suggestions, not rules, but they explain why a clinic needs your scan before it can name the procedure and price.
A Cochrane review found that, where 4–9 mm of bone remained, the evidence was insufficient to say whether sinus lifting was more or less successful than placing short implants (5–8.5 mm) up to one year after loading, with more complications at sinus-lift sites (Cochrane, 2014). Ask whether a short implant is an option. If a sinus lift is planned, read our guide to flying after implant, extraction or sinus surgery before you book the return flight.
Other ways a graft may be avoided
- Short implants. The Cochrane augmentation review also concluded that short implants appear to be a better alternative to vertical bone grafting of resorbed lower jaws (Cochrane, 2009).
- Full-arch designs. All-on-4 angles the back implants into the denser bone at the front of the jaw, so some people told they lack bone can avoid grafting. See our All-on-4 guide.
- Ridge preservation at extraction. Filling the socket with graft material after an extraction may reduce ridge shrinkage at six months, but a 2021 Cochrane review rated the evidence very uncertain and found no evidence that it reduces the need for grafting later (Cochrane, 2021).
None suits every case; ask which options were considered and why. See also: what zygomatic implants are and who needs them.
What grafting does to your timeline
Cambridge University Hospitals says that if only minimal grafting is needed, it can be done at the time of implant placement (CUH). Leeds says that if more bone is needed, grafting is done several months before the implant (Leeds), and Guy’s and St Thomas’ says a bone graft might add four to six months to treatment (GSTT).
So there are three patterns: no graft; a graft placed with the implant; or a staged graft that heals before the implant goes in, which can mean an extra trip. For planning trips around healing, see dental implants in Turkey: one trip or two?
How to get grafting into the quote, not added at the chair
“The price went up when I arrived” usually means the first quote was written before anyone measured the bone. A headline implant price, such as our planning range of €350–800 for a single implant, often covers the implant itself; grafting and sinus lifts are usually extra, and the abutment and crown may be too.
This guide gives no price for grafts or sinus lifts, because they depend on the case. What changes the cost:
- the number of sites and the size of each defect;
- the material and membrane, and whether your own bone is taken from a second site;
- for a sinus lift, open or closed, one side or both;
- whether the graft is staged (an extra visit), sedation, and who operates.
Ask for a written, tooth-by-tooth quote that names each line:
| Line in the quote | What to ask |
|---|---|
| Diagnostics | Is a CBCT included, and will I get a copy of the files? |
| Extractions and ridge preservation | Which teeth, and is socket grafting proposed? At what price? |
| Bone graft | Which sites, which material and membrane, price per site, at implant surgery or staged? |
| Sinus lift | Open or closed, which side, price per side, and is the implant placed at the same time? |
| Implant, abutment and crown | Which implant system, and which parts are included? |
| If the plan changes | Will you show me the scan, put the new price in writing and refund the deposit if I decline? |
Without a scan, ask for conditional prices: “if a graft is needed at this site, it costs X; if a sinus lift is needed, Y.” Figures agreed in writing before you travel reduce the risk of surprises. Compare quotes line by line; the dental cost index gives context.
Grafting also adds risk: CUH lists a graft that fails to take, more likely in smokers, and rarer nerve-related numbness (CUH). Ask who looks after you at home; see dental guarantees and aftercare.
Frequently Asked Questions
Does every dental implant need a bone graft?
No. A graft is needed only when there is not enough healthy bone, in height or width, to hold the implant in the right position. It is more likely when a tooth was lost long ago, after gum disease, and in the upper back jaw below the sinus. A 3D scan is the usual way to find out.
How can I find out whether I need a bone graft before I travel to Turkey?
Get a cone beam CT (CBCT) scan, or send a recent one. NHS implant services such as Leeds Teaching Hospitals usually request this 3D scan because it shows how much bone there is and where nerves, sinuses and neighbouring roots sit. A panoramic X-ray (OPG) is two-dimensional and cannot show the width of the bone; photographs cannot show bone at all.
Is a sinus lift the same as a bone graft?
A sinus lift is a type of bone graft for the upper back jaw. The membrane lining the floor of the sinus is raised and graft material placed underneath to add height. It is done either through a window in the side of the sinus (open, or lateral) or through the implant site (closed, or crestal).
Does a bone graft mean I need an extra trip to Turkey?
Not always. A small graft can often be placed with the implant. A larger graft is usually done several months before the implant, which can add a visit. Ask how many trips your plan needs before you book flights.
Why did my implant quote go up after the scan at the clinic?
Usually because the first quote was given before anyone measured your bone, and the scan showed that a graft or sinus lift is needed. Ask to see the scan and measurements, get the new plan and price in writing, and take time to decide. Agreeing conditional grafting prices before you travel reduces the risk of this.
Sources
- Leeds Teaching Hospitals NHS Trust: dental implants (patient information)
- Guy’s and St Thomas’ NHS Foundation Trust: having a dental implant
- Cambridge University Hospitals: bone grafting for dental implants
- Tan WL et al. A systematic review of post-extractional alveolar hard and soft tissue dimensional changes in humans. Clin Oral Implants Res. 2012;23 Suppl 5:1-21
- Ferraz MP. Bone grafts in dental medicine: an overview of autografts, allografts and synthetic materials. Materials (Basel). 2023;16(11):4117
- Lyu M et al. Maxillary sinus floor augmentation: a review of current evidence on anatomical factors and a decision tree. Int J Oral Sci. 2023
- Esposito M et al. Interventions for replacing missing teeth: augmentation procedures of the maxillary sinus. Cochrane Database of Systematic Reviews 2014
- Esposito M et al. Interventions for replacing missing teeth: horizontal and vertical bone augmentation techniques for dental implant treatment. Cochrane Database of Systematic Reviews 2009
- Atieh MA et al. Interventions for replacing missing teeth: alveolar ridge preservation techniques for dental implant site development. Cochrane Database of Systematic Reviews 2021
Comparing clinics? Every profile shows whether we found the clinic on the Ministry of Health authorisation list. Browse clinics or read how the license check works.